TMS Billing Services · Nevada · For TMS Clinics and Interventional Psychiatry Practices
TMS Billing Services in Nevada
Get the full course approved and every session paid. TMS therapy medical billing and coding services built around authorizations, session counts, and payer coverage rules.
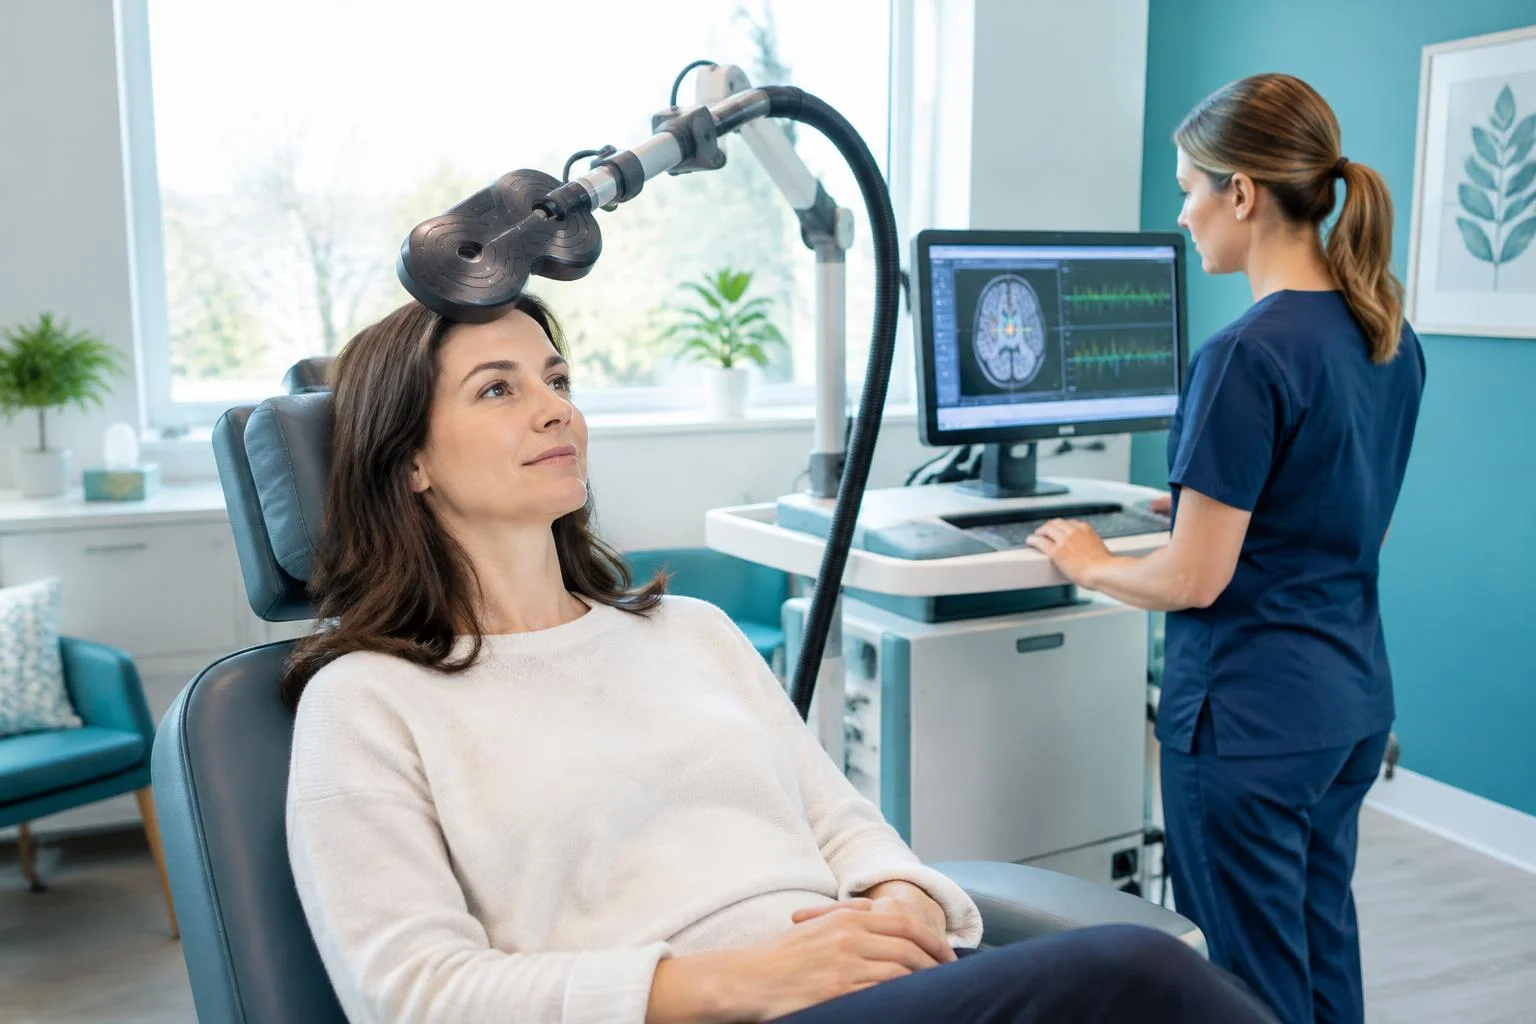
Nevada Medical Billing provides TMS billing services for transcranial magnetic stimulation clinics, psychiatric practices, and interventional mental health centers across Nevada. We handle what decides whether a TMS course gets paid: coverage criteria, prior authorization for the full course, session tracking against approved units, 90867, 90868, and 90869 coding, motor threshold documentation, and denial appeals. We bill Medicare, Medicare Advantage, Nevada Medicaid and its five managed care plans, TRICARE, and commercial insurers.
Share a few details and a TMS billing specialist will review your authorizations, session counts, and denials with you.
Full-course authorizations tracked session by session90867, 90868, and 90869 coded to payer rulesRe-treatment and taper approvals filed on timeHIPAA compliant, BAA signed day oneFull-course authorizations tracked session by session90867, 90868, and 90869 coded to payer rulesRe-treatment and taper approvals filed on timeHIPAA compliant, BAA signed day one
36-session courses tracked end to end
95%+ clean claims target
Under 35 days in A/R target
5 Nevada Medicaid MCOs
TMS billing
Why TMS Billing Is Different From Other Psychiatry Billing
TMS billing is different because you aren't billing a visit, you're billing a course. One patient becomes 30 to 40 claims over six to nine weeks, all riding on a single authorization that a payer approved for a set number of sessions. If the approval, the session count, or the motor threshold documentation slips, every remaining session in the course is at risk.
Payers also treat TMS as a high-review service. They want proof of treatment-resistant depression, documented failed medication trials with dose and duration, and validated symptom scores before they approve the first session, and again before any extension or re-treatment.
TMS billing
Where TMS Clinics Lose Revenue
01
Authorizations That Run Out Before the Course Ends
When a patient misses sessions or needs taper sessions, the course runs longer than the approval. Sessions given after the authorized count or end date are usually denied, and appeals for them rarely succeed.
02
Thin Failed-Trial Documentation
The most common reason TMS authorizations are denied is a failed-trial history that doesn't list each antidepressant's dose, duration, and outcome. A packet that says "failed multiple medications" isn't enough.
03
90867 Billed More Than Once
The initial session code with cortical mapping is billed once per course. Billing it again for later mapping sessions triggers denials; re-mapping uses 90869.
04
Missing Per-Session Detail
Payers can ask for coil location, motor threshold, stimulation parameters, and patient response for each session. Gaps found in an audit lead to recoupments months after payment.
05
Re-Treatment Billed Like a New Course
Patients who relapse may qualify for another course, but most payers apply separate re-treatment criteria, such as a documented response to the first course. Re-treatment requests built like new cases get denied.
06
Carve-Outs and the Wrong Payer
Many commercial plans route TMS through a behavioral health vendor. Authorizations requested from the medical plan, or claims sent there, are rejected.
TMS billing
How a TMS Course Is Billed
A standard TMS course for depression runs daily on weekdays for about six weeks, then tapers, for roughly 36 sessions in total. Here's how that course turns into claims.
One TMS course becomes 30 to 40 claims under one approval
1
Evaluation
90792 or E/M
baseline scores
2
First session
90867, once
motor threshold
3
Daily treatment
90868 per session
90869 if re-mapped
4
Taper
90868 per session
fewer per week
5
Course end
outcome scores
re-treat criteria
One authorization: about 36 sessions, each tracked
Losing sessions at the end of a course? Get a Free TMS Billing Audit and we'll match your session counts to your authorizations.
Initial TMS treatment, including cortical mapping, motor threshold determination, delivery, and management
Once per course
Billed only on the first session; not repeated for later mapping
90868
Subsequent treatment delivery and management, per session
Each session after the first
Count matched to the authorization; one per day
90869
Subsequent motor threshold re-determination with delivery and management
Only when threshold is re-measured
Documented reason for re-mapping; not billed with 90868 the same day
90792 or 99202–99215
Psychiatric evaluation before the course, and periodic E/M visits during it
Per payer policy
Separate E/M on a treatment day only when significant and separately documented, with modifier 25
90833, 90836, 90838
Psychotherapy add-ons with an E/M
When therapy is separately provided
Time distinct from the TMS session
Diagnosis coding must support covered indications, most often major depressive disorder, single or recurrent episode, coded to severity (such as F32.2 or F33.2). Unspecified depression codes are a common denial trigger.
Newer TMS techniques with Category III codes are generally not covered by payers; we confirm coverage before treatment.
TMS billing
What Payers Require to Cover TMS
Most payers, including Medicare, cover TMS for adults with treatment-resistant major depressive disorder when their criteria are met. Nevada's Medicare contractor, Noridian, publishes its criteria in LCD L37086. Commercial and Medicaid plans usually follow similar criteria and add their own authorization forms.
What Payers Require to Cover TMS
Typical criterion
What we document
Confirmed diagnosis of major depressive disorder, coded to severity
Diagnosis and current episode details
Failed antidepressant trials
Each medication with dose, duration, and reason it failed or wasn't tolerated
Trial of psychotherapy (required by many plans)
Type, duration, and outcome
Validated symptom scores
Baseline PHQ-9, HAM-D, MADRS, or BDI
No contraindications
Screening for seizure history and metal implants near the coil
Treatment plan
Device, protocol, and planned number of sessions
TMS billing
TMS Indications, Devices, and What Payers Cover
TMS Indications, Devices, and What Payers Cover
Indication or approach
Typical devices
Coverage outlook
Treatment-resistant major depression
NeuroStar, BrainsWay Deep TMS, MagVenture, Magstim
Widely covered when criteria are met
Obsessive-compulsive disorder (deep TMS)
BrainsWay Deep TMS
Coverage varies by plan; many cover depression only
Theta burst protocols (iTBS)
Devices cleared for theta burst
Often covered under the same codes when the device and protocol are FDA-cleared
Accelerated TMS (multiple sessions per day)
Specialized protocols such as SAINT
Frequently limited or not covered; verified plan by plan
Maintenance TMS
Any
Usually not covered without strong criteria
We verify the device, indication, and protocol against each payer's policy before the first session, so a course is never started on a service the plan won't pay for.
TMS billing
TMS Therapy Medical Billing and Coding Services, End to End
Our TMS billing services cover the full course, from the first benefits check to the last taper session. Choose complete revenue cycle management for your TMS program or the services you need.
01
TMS Benefits Verification
We confirm TMS coverage, carve-out vendor, covered indications, session limits, copays, deductibles, and whether the plan accepts your device and protocol. Eligibility Verification
02
Prior Authorization Packets That Get Approved
We build the medical necessity packet: diagnosis coded to severity, each failed antidepressant with dose, duration, and outcome, psychotherapy history, baseline scores, and treatment plan. We prepare peer-to-peer reviews for your psychiatrist when payers request them. Prior Authorization
03
Course and Session Tracking
Every approved session is tracked against the authorization's count and end date. You're alerted before a course outruns its approval, so extensions are filed in time.
04
TMS Coding and Charge Entry
We bill 90867 once, 90868 per session, and 90869 only when threshold is re-measured, and check each claim against session notes for coil location, motor threshold, and parameters.
05
Clean Claim Submission
Claims are scrubbed for frequency rules, authorization numbers, diagnosis specificity, and payer edits, then submitted within 48 hours.
06
TMS Denial Management and Appeals
We appeal medical necessity, session-limit, and frequency denials with treatment history and session documentation, and use mental health parity rules when coverage limits are stricter than for medical care. Denial Management
07
Payment Posting and Underpayment Review
We post payments daily and compare each session's payment to your contracted rate. Payment Posting
08
A/R Follow-Up
We work every open TMS claim, starting with sessions closest to timely filing limits. AR Follow-Up
09
Re-Treatment and Extension Requests
When a patient relapses or needs more sessions, we build the request around the payer's re-treatment criteria, including documented response to the prior course.
10
TMS Clinic Launch Support
Opening a TMS clinic or adding TMS to a psychiatry practice? We handle payer enrollment, coverage research by device and indication, intake checklists that capture what authorizations need, and billing setup before your first patient.
TMS billing
TMS Prior Authorization and Course Tracking
Approval is where TMS revenue starts. We manage it as a timeline, not a single form.
01
Before the consult ends: Intake captures medication history with dose and duration, prior therapy, and baseline scores, so the packet is complete on day one.
02
At submission: Requests to Medicare Advantage and Medicaid plans are tracked against the federal prior authorization decision windows that took effect in 2026: 7 calendar days for standard requests and 72 hours for expedited ones.
03
During the course: Sessions used, sessions remaining, and the approval end date are updated after every treatment.
04
Before the end: Extension or taper requests go out with progress scores before the approval runs out.
05
After the course: Outcome scores are saved to support future re-treatment requests.
Let's talk
Find Out Where Your TMS Revenue Is Slipping
01
Session count vs authorization review for active patients
02
Failed-trial documentation check on recent denials
Interventional psychiatry centers (TMS and Spravato)
Both treatment lines under one billing team
Deep TMS and OCD programs
Indication-specific coverage checks before treatment
Multi-site TMS groups
Location-level reporting and standardized authorization workflows
New TMS clinics
Launch support from payer enrollment to first claim
TMS billing
Nevada Payers We Bill for TMS
Nevada Payers We Bill for TMS
Payer category
Plans
Medicare
Noridian Healthcare Solutions (Jurisdiction E), under LCD L37086
Medicare Advantage
Health Plan of Nevada/UnitedHealthcare, Humana, Aetna, Anthem, and other MA plans
Nevada Medicaid
Fee-for-service Nevada Medicaid, with coverage verified before treatment
Nevada Medicaid managed care
Anthem Blue Cross and Blue Shield, CareSource, Health Plan of Nevada, Molina Healthcare of Nevada, SilverSummit Healthplan
Commercial
Anthem BCBS Nevada, UnitedHealthcare/Optum, Aetna, Cigna, Hometown Health, Prominence Health Plan
Behavioral health carve-outs
Vendors that manage TMS approvals for commercial plans
Military
TRICARE
TMS billing
We Work Inside Your TMS and EHR Systems
We bill from the systems TMS clinics already use, including NeuroStar TrakStar session data, AdvancedMD, Valant, Tebra/Kareo, DrChrono, athenahealth, eClinicalWorks, Osmind, and SimplePractice. No software change needed. EHR Integration
Also offering Spravato? See our Spravato billing services: the same team can manage both treatment lines.
Free TMS billing audit: We review 90 days of TMS claims, authorizations, session counts, and denials.
02
Secure setup: We sign a BAA and connect to your EHR, TMS system data, clearinghouse, and payer portals.
03
Payer and policy mapping: We confirm each payer's criteria, carve-out vendor, and session limits, including Noridian's LCD for Medicare patients.
04
Course inventory: Every active patient's approval, sessions used, and end date go into tracking before go-live.
05
Go-live: Daily session coding, scrubbing, and submission begin.
06
Legacy A/R cleanup: We work old TMS claims in parallel so nothing ages out.
07
Monthly review: KPI report and a call with your dedicated account manager.
TMS billing
What Results Can Your TMS Clinic Expect?
These are the performance standards we manage your TMS revenue cycle to, based on industry best practices.
What Results Can Your TMS Clinic Expect?
KPI
What it measures
Best-practice target
First-pass clean claim rate
TMS claims paid without rework
95% or higher
Denial rate
Claims denied on first submission
Under 5%
Days in A/R
Average time from session to payment
Under 35 days
Sessions without approval
Sessions given outside an active authorization
Zero, with course tracking
Authorization packet completeness
Requests sent with full failed-trial detail
Every request
Claim submission
Time from session to claim sent
Within 48 hours
What a Free TMS Billing Audit Typically Uncovers
01
Taper sessions given after the authorization ended
02
Authorization denials caused by missing medication doses or durations
03
90867 billed again instead of 90869
04
Unspecified depression codes on TMS claims
05
Commercial patients authorized through the medical plan instead of the carve-out vendor
06
Session payments below contracted rates
TMS billing
How Much Do TMS Billing Services Cost?
TMS billing is usually priced as a percentage of monthly collections, commonly 4–9% for behavioral health. Where your clinic falls depends on new patients per month, payer mix, and how much authorization and re-treatment work is involved. Unlike flat-fee staffing models, a percentage fee means you pay more only when you collect more. There are no setup fees, the agreement is month-to-month with 30-day notice, and you get a fixed quote after your free audit.
Worried About Switching? Here's How We Remove the Risk
01
"Patients mid-course will lose sessions." Every active authorization and session count is loaded before go-live.
02
"Our cash flow will drop." We work old TMS claims in parallel while new ones go out.
03
"We'll lose visibility." You see every claim in your system, plus a monthly review call.
04
"We're locked in." You're not. The agreement is month-to-month with 30-day notice.
TMS billing
Compliance Standards for TMS Billing
TMS billing follows CPT and ICD-10-CM guidelines, Medicare LCD and billing article requirements, NCCI edits, payer medical policies, mental health parity rules, and HIPAA. We sign a Business Associate Agreement before accessing any patient data.
TMS billing
Why Nevada TMS Clinics Choose Nevada Medical Billing
01
Course-level control: Every session tracked against its approval.
02
Approvable packets: Failed-trial histories built to each payer's criteria.
03
Correct coding: 90867, 90868, and 90869 frequency rules on every claim.
04
Interventional psychiatry depth: TMS, Spravato, and medication management billed by one team.
05
Nevada payer expertise: Noridian, five Medicaid MCOs, carve-out vendors, and local commercial plans.
06
No lock-in: Month-to-month agreement with 30-day notice.
TMS billing
TMS Billing Services Across Nevada
01
Las Vegas: Standalone TMS clinics, interventional psychiatry centers, and multi-site groups offering TMS and Spravato. Las Vegas billing
TMS billing services manage the revenue cycle for transcranial magnetic stimulation: benefits verification, prior authorization, session tracking, coding, claim submission, payment posting, denial appeals, and A/R follow-up for the full course.
90867 for the initial session with cortical mapping and motor threshold, 90868 for each later treatment session, and 90869 for sessions where motor threshold is re-determined.
A typical approved course for depression is about 36 sessions, including taper, though limits vary by payer. Sessions beyond the approved count need an extension before they're given.
Yes, for adults with treatment-resistant major depressive disorder who meet Noridian's criteria in LCD L37086.
Usually a confirmed major depressive disorder diagnosis coded to severity, several failed antidepressant trials with dose and duration, often a psychotherapy trial, baseline symptom scores, and a treatment plan.
It varies. Since 2026, Medicare Advantage and Medicaid plans must decide standard prior authorization requests within 7 calendar days and expedited ones within 72 hours. A complete packet avoids extra requests for information.
Only when a significant, separately identifiable service is documented, usually with modifier 25. Routine monitoring during TMS is part of the TMS code.
Some plans cover it, but many limit TMS coverage to depression. We verify each patient's plan before treatment begins.
Yes. We build re-treatment requests around payer criteria, which usually require documented response to the previous course.
Yes. We handle payer enrollment, coverage research by device and indication, intake checklists, and billing setup before your first patient.
Most behavioral health billing is priced at 4–9% of collections. We give a fixed quote after a free audit.